

Efficacy Data for WELIREG® (belzutifan) in Certain Adults With Advanced Renal Cell Carcinoma with a Clear Cell Component (ccRCC)

PFS & OS
- 25% reduced risk of disease progression or death shown with WELIREG vs everolimus (HRa=0.75; 95% CI, 0.63–0.90; Pb=0.0008)
- Events observed: 257/374 (69%) with WELIREG vs 262/372 (70%) with everolimus
- Median PFSc: 5.6 months (95% CI, 3.9–7.0) with WELIREG vs 5.6 months (95% CI, 4.8–5.8) with everolimus
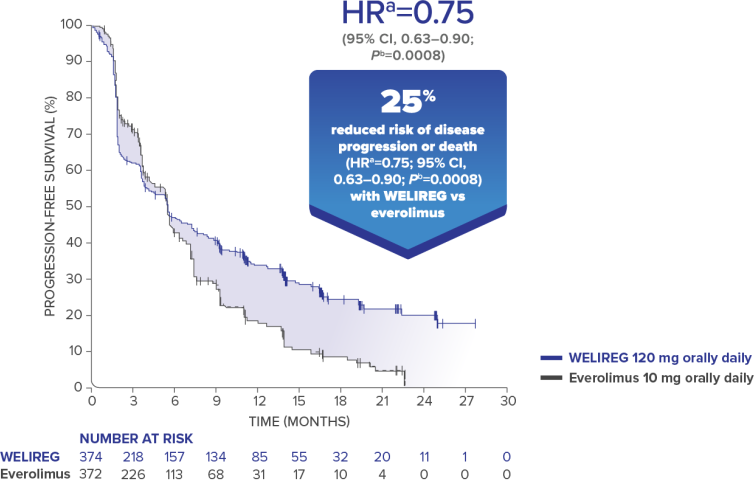
At final analysis, OS was not statistically significant with WELIREG vs everolimus
(HRa=0.92; 95% CI, 0.77–1.10; Pd=NS)
- Events observed: 254/374 (68%) with WELIREG vs 259/372 (70%) with everolimus.
- Median OS: 21 months (95% Cl, 18–24) with WELIREG vs 18 months (95% Cl, 16–22) with everolimus.
Based on the stratified Cox proportional hazard model.
One-sided P-value based on stratified log-rank test compared with the significance boundary of 0.0021.
From product-limit (Kaplan-Meier) method for censored data.
Based on stratified log-rank test.
ccRCC = renal cell carcinoma with a clear cell component; CI = confidence interval; HR = hazard ratio; NS = not statistically significant; OS = overall survival; PD-1/L1 = programmed death receptor-1 (PD-1)/programmed death-ligand 1 (PD-L1); PFS = progression-free survival; VEGF-TKI = vascular endothelial growth factor tyrosine kinase inhibitor.
ORR
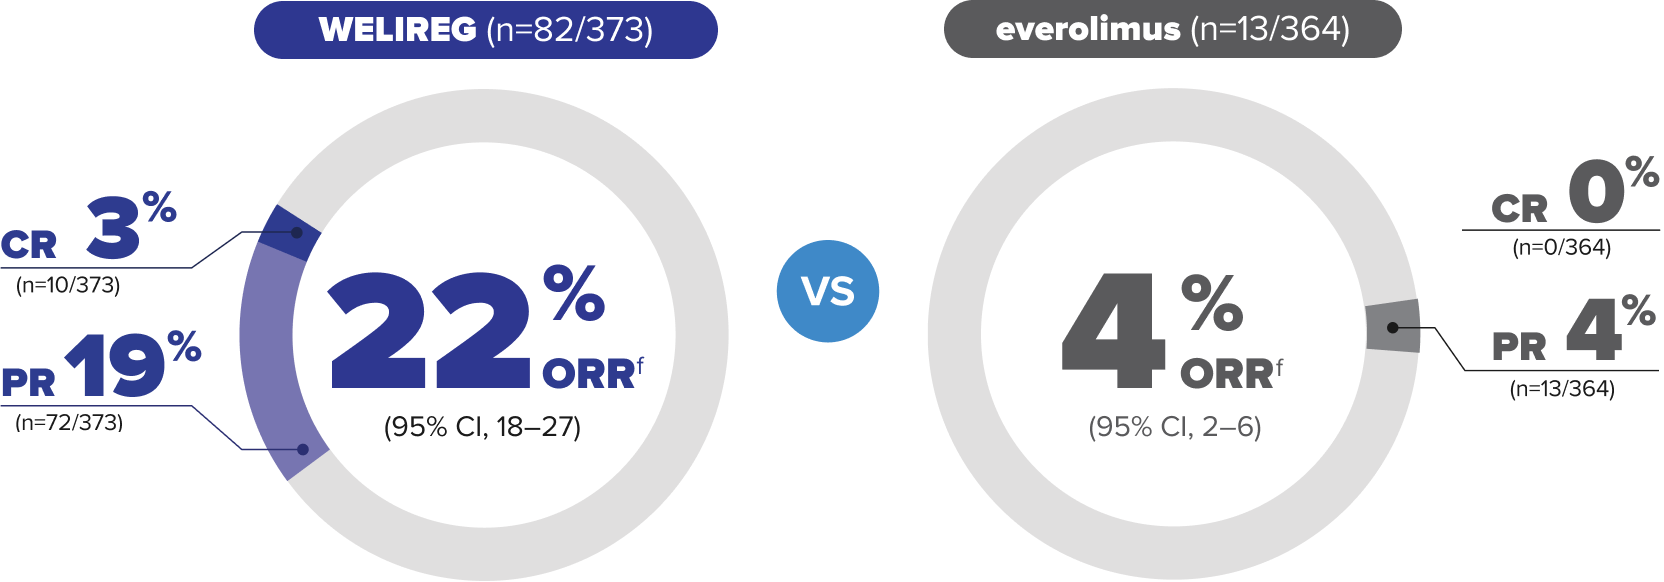
30% of patients who responded (25/82) with WELIREG had a duration of response that lasted ≥12 months
One-sided P-value based on stratified Miettinen and Nurminen (M&N) method.
ORR measured by blinded independent central review using RECIST v1.1.
CR = complete response; ORR = objective response rate; PR = partial response; RECIST v1.1 = Response Evaluation In Solid Tumors v1.1.
Study Design
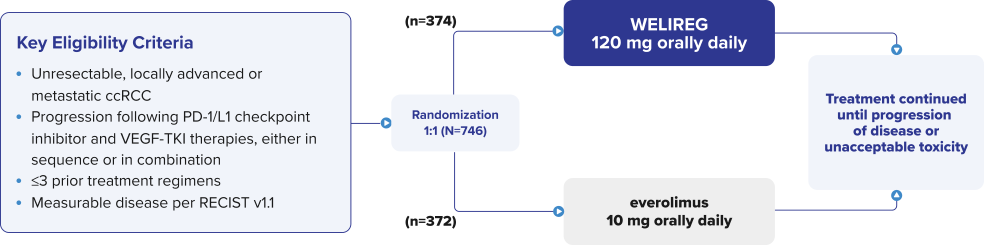
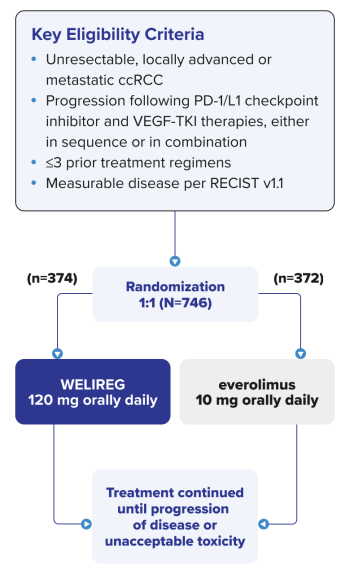
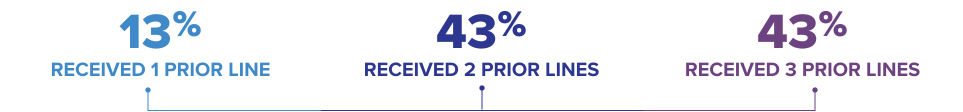

Of all evaluated patients, 49% received 2 to 3 prior VEGF receptor–targeted therapies

2L+ = second line or later; ECOG PS = Eastern Cooperative Oncology Group performance status; IMDC = International Metastatic Database Consortium; VEGF = vascular endothelial growth factor.
Additional resources
WELIREG may be considered as early as the second line for your appropriate adult patients with advanced ccRCC following treatment with both anti–PD-1/L1 and VEGF-TKI therapies